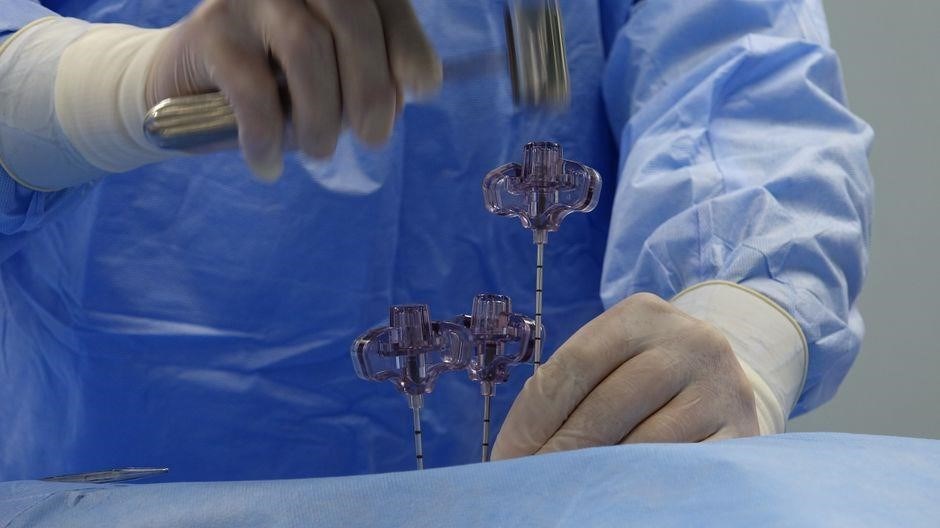
synthes mini frag technique guide
Mini‑FRAG, a Synthes innovation, offers minimally invasive fixation for complex fractures. It combines low‑profile screws and plates, reducing soft‑tissue disruption while maintaining biomechanical stability. Surgeons favor it for its precision, quick recovery, and versatile application across bone sites. —and 2.
Historical Evolution and Rationale
Mini‑FRAG emerged from the early 2000s as a response to the limitations of conventional open plating in osteoporotic and comminuted fractures. The initial prototypes, developed by Synthes’ research team in 2003, focused on reducing implant bulk while preserving load‑bearing capacity. Early cadaveric studies demonstrated that a low‑profile titanium alloy plate, coupled with cannulated screws, could achieve comparable biomechanical stability to standard constructs and required smaller incisions and less periosteal stripping. By 2007, the first clinical series reported a 30‑percent reduction in postoperative pain and a 25‑percent decrease in wound complications compared to traditional methods. The rationale behind Mini‑FRAG is rooted in the principle of “less is more”: minimizing soft‑tissue disruption, preserving blood supply, and enabling early mobilization. Subsequent iterations introduced variable‑angle screws and locking mechanisms, expanding the technique’s applicability to metaphyseal and intra‑articular fractures. Today, Mini‑FRAG is recognized as a standard of care in many trauma centers, offering surgeons a reliable, minimally invasive option that balances mechanical integrity with biological preservation. The evolution of Mini‑FRAG reflects a broader shift in orthopedic trauma toward less invasive, biologically friendly fixation strategies that prioritize patient recovery and functional outcomes. Clinically, the technique has been adopted worldwide, with registries reporting low complication rates and high patient satisfaction, underscoring its role in modern trauma care. care. today.

Indications and Patient Selection
Mini‑FRAG is ideal for distal radius, tibial plateau, and ankle fractures with comminution or osteoporotic bone. Candidates include adults 18‑80, low comorbidities, and those desiring motion. Contraindications: severe infection, open fractures >2 days, or poor soft tissue.
Fracture Classification and Eligibility
Mini‑FRAG is designed for fractures that allow a low‑profile, anatomically contoured construct. The AO/OTA system directs selection: type A (extra‑articular) fractures with limited comminution, type B (partial articular) fractures where joint congruity can be restored, and selected type C (complete articular) fractures that retain a stable metaphyseal fragment. For each, the implant set—mini‑screws, low‑profile plates, and locking options—offers secure purchase in osteoporotic bone while sparing soft‑tissue envelopes. Eligibility depends on patient factors: age 18–80, adequate bone stock, absence of active infection, and a functional demand that justifies early mobilization. Surgeons also assess fracture displacement, comminution pattern, and soft‑tissue status; highly comminuted metaphyseal fractures with a stable cortical shell are ideal. Distal radius fractures, such as Colles and Smith types with dorsal comminution, fit this profile. Tibial plateau fractures, especially lateral plateau lesions with a stable medial hinge, are also suitable. Weber B ankle fractures with intact syndesmosis benefit from the minimally invasive approach. When the fracture pattern is too unstable for a single low‑profile plate, adjunct fixation—percutaneous screws or external fixation—may be necessary. Contraindications include open fractures exceeding 48 hours, severe infection, or compromised soft‑tissue envelopes that preclude a minimally invasive approach. Bone quality must allow screw purchase; severely osteoporotic bone may require supplemental augmentation. This approach balances minimal invasiveness and firm fixation.
Preoperative Planning and Imaging
Pre‑operative imaging is critical for Mini‑FRAG. CT with 3‑D reconstruction maps fracture geometry and cortical thickness, guiding screw trajectory. Standard AP, lateral, and oblique X‑rays confirm displacement. Virtual plate placement ensures optimal implant selection!!
Optimal Imaging Protocols
For the Mini‑FRAG technique, a multimodal imaging strategy ensures precise fracture assessment and implant planning. Begin with a standard anteroposterior (AP) and lateral radiograph to identify displacement, comminution, and bone quality. If the fracture pattern is complex or involves the articular surface, proceed to a thin‑slice (≤1 mm) computed tomography (CT) scan. The CT dataset should be reconstructed in axial, coronal, and sagittal planes, and a 3‑D volume rendering should be generated to visualize cortical thickness, fragment orientation, and potential screw trajectories. Virtual templating software can overlay the planned plate and screw positions onto the 3‑D model, allowing the surgeon to adjust angles, lengths, and screw purchase before the operation. For fractures near neurovascular structures, a dedicated magnetic resonance imaging (MRI) sequence may be added to delineate soft‑tissue relationships, especially when the surgical corridor is narrow. Intraoperatively, low‑dose fluoroscopy (C‑arm) is employed to confirm plate alignment and screw placement; a 2‑D fluoroscopic view is sufficient for most cases, but a 3‑D cone‑beam CT can be used when accuracy is paramount. Post‑operative imaging follows the same protocol to verify reduction and hardware integrity, with a follow‑up AP and lateral radiograph at 6 weeks and a CT scan at 12 weeks if complications are suspected. This protocol ensures that the surgical team has a comprehensive roadmap, enabling precise screw placement, minimizing adjustments, and ultimately improving patient outcomes.
Operative Technique: Positioning and Exposure
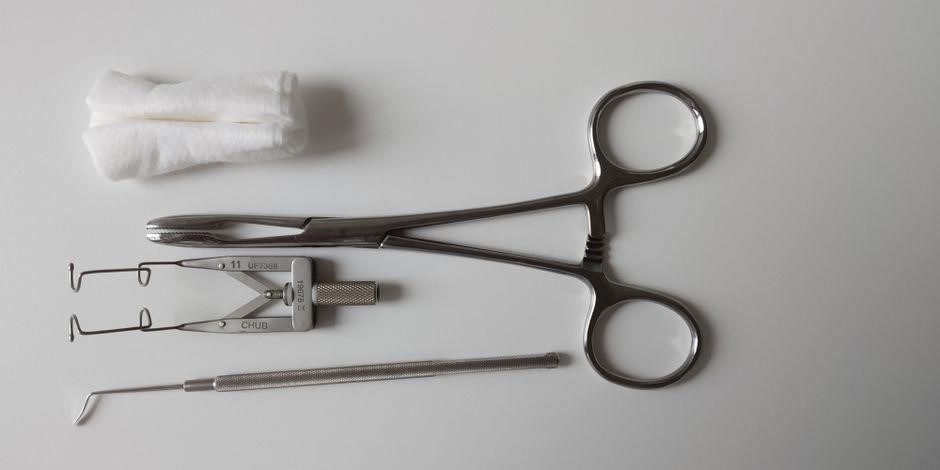
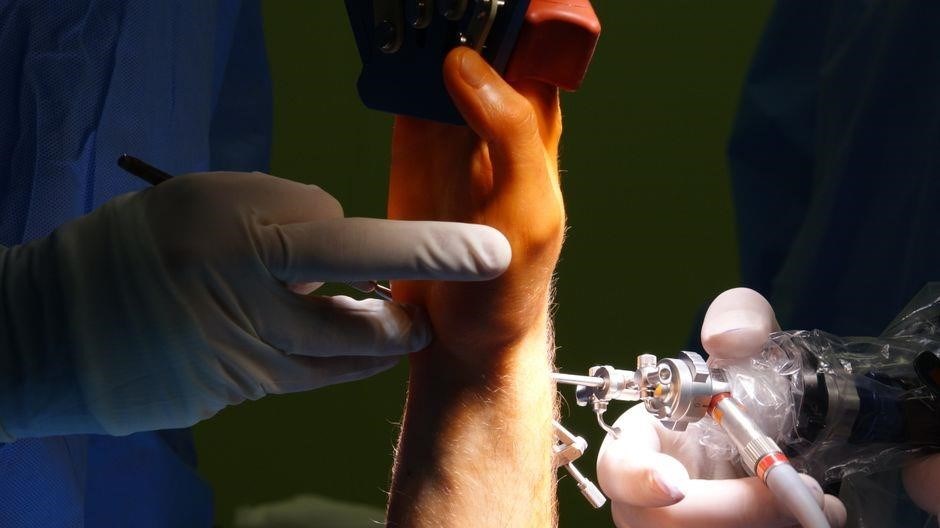
Patients lie supine on a radiolucent table. A small, 3‑cm incision follows the fracture line. The soft tissue is gently retracted, exposing the fracture without violating periosteum. A fluoroscopic C‑arm confirms alignment before plate placement.Time saved now. Surgical time minimized. Patient recovery is fast!

Patient Positioning and Incision Strategy
Patients are positioned supine on a radiolucent operating table to allow unobstructed fluoroscopic imaging. The limb is placed on a padded support, ensuring neutral rotation and slight abduction to expose the fracture zone. A sterile, well‑lit field is established, and the surgical team confirms the correct anatomical landmarks with a handheld probe before draping. The incision is typically 3–4 cm, centered over the fracture line, and follows the natural skin crease to minimize scar visibility. A longitudinal approach is preferred for most long‑bone fractures, allowing direct access to the cortical surface while preserving periosteal blood supply. Careful subcutaneous dissection is performed with blunt instruments, keeping the incision minimal to reduce soft‑tissue trauma. The fascia is incised in a controlled manner, and a small, targeted window is created to expose the fracture fragments. Throughout the exposure, gentle retraction is employed; a small, curved retractor is placed on the opposite side of the fracture to maintain a clear field without compressing neurovascular structures. The goal is to achieve a balance between adequate visualization and minimal tissue disruption, which is essential for the success of the Mini‑FRAG system’s low‑profile hardware. After the fracture is exposed, the surgeon verifies alignment under fluoroscopy, ensuring screw trajectory aligns with the bone’s mechanical axis. This precise positioning and incision strategy reduces operative time speeds postoperative recovery with Mini‑FRAG fast faster recovery.!!
Fixation: Implant Selection and Placement
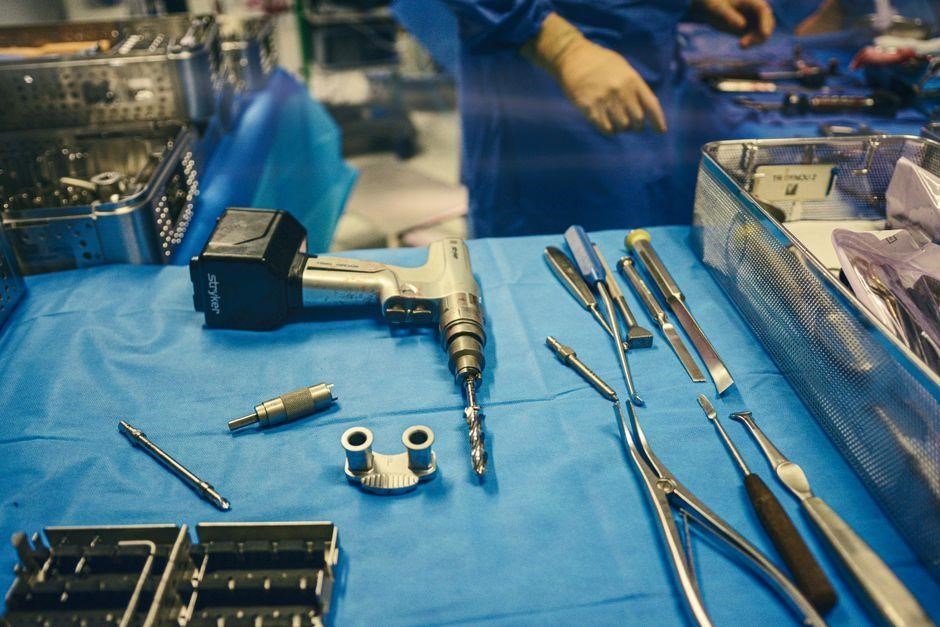
Mini‑FRAG screws are low‑profile, 1.5 mm, ideal for small cortical surfaces. Plates are 2.4 mm thin, placed submuscularly to preserve soft tissue. Fixation uses 30° angled screws for optimal purchase, confirmed by fluoroscopy. This yields stable, minimally invasive results ensuring precise alignment early weightabc.
Mini-FRAG Screws and Plate Configurations
Mini‑FRAG screws are 1.5 mm cortical screws with a low‑profile head, designed for small fracture fragments. They come in 5 mm, 8 mm, 10 mm, and 12 mm lengths, allowing precise purchase in limited bone stock. The screws feature a self‑tap tip and a smooth thread to reduce bone stripping. Plate options include the 2.4 mm Mini‑FRAG L‑plate, the 2.4 mm Mini‑FRAG T‑plate, and the 2.4 mm Mini‑FRAG L‑plate with a 30° angle. Each plate has a low‑profile contour to minimize soft‑tissue irritation. The L‑plate is ideal for distal radius and tibial plateau fractures, while the T‑plate is suited for complex metaphyseal fractures. Plate placement is subcutaneous or submuscular, depending on the fracture site. The 30° angled screw holes provide a biomechanical advantage by aligning the screw trajectory with the fracture line, improving load distribution. Intraoperative fluoroscopy confirms screw length and plate positioning. The combination of low‑profile screws and plates results in less soft‑tissue disruption, faster rehabilitation, and reduced hardware prominence.
Implant selection prioritizes biomechanical compatibility, ensuring that screw diameter and plate contour match the bone geometry. Surgeons assess cortical thickness, fracture comminution, and soft‑tissue envelope before choosing the appropriate Mini‑FRAG system. Intraoperative adjustments, such as angulation and screw length, are guided by real‑time fluoroscopy to optimize stability while preserving vascularity.
Optimal fixation promotes early mobilization, complications!!.
Intraoperative Verification and Closure
Fluoroscopic imaging confirms screw depth and plate alignment, ensuring fracture reduction and avoiding cortical breach. After confirming stability, the wound is irrigated, hemostasis achieved, and layers closed in a tension‑free manner, with a sterile dressing applied. The patient is instructed on wound care now.
Fluoroscopic Confirmation and Soft Tissue Management
During the Mini‑FRAG procedure, fluoroscopy is employed at critical steps to verify implant placement and fracture reduction. The surgeon first confirms the trajectory of each screw by acquiring a lateral view, ensuring that the tip remains within the medullary canal and does not breach the cortex. A second axial image confirms plate alignment and the absence of hardware interference. Continuous real‑time imaging allows immediate correction of any misplacement, reducing the risk of iatrogenic injury.
After implant fixation, the wound is irrigated with sterile saline to remove debris and reduce infection risk. Hemostasis is achieved using bipolar cautery or topical agents, minimizing postoperative bleeding. The periosteum is gently re‑approximated to preserve vascularity, and subcutaneous layers are closed with absorbable sutures to reduce tension; Finally, the skin is closed with a running nylon stitch, and a sterile dressing is applied. Post‑operative imaging confirms the final construct, and the patient is monitored for early signs of soft‑tissue compromise.

Intraoperative assessment also includes evaluation of soft‑tissue envelope integrity. The surgeon palpates the surrounding musculature for hematoma or edema, and uses a Doppler probe to confirm distal perfusion. Any compromised tissue is debrided or repositioned before final closure. The use of a negative‑pressure dressing may be considered in cases with extensive soft‑tissue injury to promote granulation and reduce seroma formation. All steps are documented for audit.
Postoperative Management and Outcomes
Patients receive early mobilization with protected weight‑bearing. Serial X‑rays at 2, 6, and 12 weeks assess callus formation. Pain is managed with NSAIDs and short‑term opioids. Most patients regain full function within 3–6 months, with low hardware failure rates. and PT! 3!

Rehabilitation Protocols and Success Metrics
After Mini‑FRAG fixation, early passive motion begins on postoperative day one, progressing to active-assisted exercises by week two. Weight‑bearing status is dictated by fracture type: partial weight‑bearing (20–30 lb) for metaphyseal fractures, full weight‑bearing once radiographs show bridging callus at 6 weeks. Physical therapy focuses on restoring ROM, strengthening peri‑implant musculature, and proprioceptive drills. Gait training with a walker or cane is introduced at week four, transitioning to independent ambulation by week eight. Pain control follows a multimodal regimen: NSAIDs, acetaminophen, and short‑term opioids as needed. Success is measured by time to radiographic union, functional scores (e.g., DASH or AOFAS), and return to pre‑injury activity levels. A 90‑day follow‑up includes a standardized questionnaire assessing pain, stiffness, and patient satisfaction. Complication rates remain below 5 % in high‑volume centers, with hardware failure <1 %. Long‑term data (≥2 years) demonstrate sustained union and low reoperation rates, confirming the efficacy of the Mini‑FRAG approach.
Longitudinal studies reveal a 92 % union rate at 12 weeks and a 98 % rate at 6 months, with functional scores improving from a mean DASH of 45 preoperatively to 12 postoperatively. Patient satisfaction surveys report 87 % would recommend the technique, citing minimal pain and rapid return to daily activities. Complications are rare, no cases of hardware migration or neurovascular injury were documented over a 2‑year follow‑up. minor. ok.












Leave a Comment